Not on air · 3 of 3 networks checked

UControl Billing ads
- ucontrolbilling.com
- Hospitals and Health Care
- US
- 9 employees
UControl Billing’s ads on LinkedIn, Meta and Google, recorded by adsrunning. Browse the latest here for free. Sign up free to see all 172. Watch UControl Billing on any plan to get each new one in your feed.
Watchlist included in every plan
What UControl Billing runs
- Single image · LinkedIn
- 6
- Google ads on 13 Oct 2026
- 4
| Network | Status | Live ads | Nov 2025LinkedIn activity · 52 weeksNov 2026 | Checked | Next step |
|---|---|---|---|---|---|
| None recorded | 0 | Checked 8 Nov 2026 | See all 172 ads → | ||
| Meta | None recorded | 0 | No active ads recorded on the Meta Ad Library | Checked 27 Oct 2026 | Collect them with the API → |
| Recently | 4 | Ads on the Google Ads Transparency Center | Checked 13 Oct 2026 | Collect them with the API → |
UControl Billing has no live LinkedIn ads. Its Facebook page had no active ads on 27 Oct 2026, and we recorded 4 Google ads on 13 Oct 2026.
Latest ads
- LINKEDIN · IMAGERecorded 2 Oct 2026
This is me right after making a $1.3M bet in Las Vegas last year. Not in a casino though. Inside Dr. Mary's clinic. She added wound care in mid 2025 and was focused on making sure the new service line was running smoothly. But by month 3, none of the $1.3M wound-care money had hit the bank yet. And the guy supplying them wound grafts started worrying before she did. He asked Dr. Mary about payment a few times. She said the biller was handling it, and since wound care was a new service line, it would take some time. By the end of the third month, he told her this kind of delay was not normal and asked if he could speak to the biller directly. He called me right after that call and said: “You need to speak to this doctor. I don’t think her biller knows what he’s doing.” He told her the same thing and said he had asked me to get in touch because I had helped a couple of his clients before with wound-care coding and billing issues. So I spoke to Dr. Mary. Shared the contract. When I followed up a week later, she said she was interested, but she had also received other offers at lower prices. So she will decide in a couple of weeks. As luck would have it, I happened to be in Vegas a week later so I went to see her in person. I told her (and her husband who joined the meeting): I'm not gonna lower my rates. We manage 35+ wound-care practices and handled over $70M in wound revenue last year. That should count more than a 1-2% difference. But I'm so sure of our expertise in wound-care I'm willing to make a bet, since we are in Vegas. (I use lame jokes all the time, sue me...) I said I would get at least 70% of those pending claims into her account by the end of the third week. If not, I would pay her instead. And I'm willing to write the cheque right now. Her husband laughed at my dramatic bet and said he liked my confidence. And I think it was him vouching for me that made her sign the contract. I got back in my car. (That is when I took the selfie) And you can't see but I was worried because I had just made a $1.3M bet. Now my team had to make sure I didn’t look like an idiot. On my way out, I had met Helen Hernandez, the practice manager, and asked her to move access as fast as possible. Credit to her, we had it by the next afternoon. When we got in, the operator panic kicked in properly. Nothing had been done. As if the biller never planned to process anything. So we literally put 10 people on the project. We had to go claim by claim, clean what needed cleaning, submit what could be submitted, and keep pressure on whatever had been allowed to sit for almost 3 months. But I was able to make good on my promise. By the end of the third week, Dr. Mary had received $900K from wound care billings. Pheww! It was a pretty close call... I don't think I have learned my lesson though 😁 I'd still bet any amount on our wound care billing services. Wanna take me up on it?
- LINKEDIN · IMAGERecorded 2 Oct 2026
A new rheumatology practice in Georgia got held up because of ONE dot. This happened to a physician who was setting up a new practice two years ago. She came to us super frustrated after her credentialing application was rejected. When we reviewed the application closely, the thing holding it up turned out to be a literal dot. The legal entity name had the dot. The version submitted in the credentialing paperwork did not. Bureaucracy at its finest...😧 Anyway, we corrected it, resubmitted it, and it was accepted. The frustrating part is how often the issue is this small in the credentialing process. Sometimes it’s a dot. Other times it’s a phone number, an address, a missing suffix, or one digit out of place — small mismatches that are easy to miss and annoying to untangle later. The actual fix took almost no time. Getting to it was the part that dragged. This is why we always recommend filling these applications using a Checklist. No matter how many times you have done it before. And if you are new to this, don't even think about winging it. If you want the Credentialing Checklist we use, just comment "CHECKLIST" and I'll send it to you. No strings attached... ----- Just want us to take over the whole Credentialing mess? Let's talk here: https://lnkd.in/e7bNd8YV
- LINKEDIN · IMAGERecorded 2 Oct 2026
By the time a practice starts seriously talking about replacing the billing company, the mood in that conversation is almost never relief. It is an overwhelming fear of change. People are not scared of “change” in some big philosophical way. They’re thinking about the stuff nobody has fully pinned down yet, and who gets stuck with it the minute this changes hands. That’s when all the half-settled stuff becomes very real. Old A/R. Claims still moving. Credentialing and auth that everyone keeps assuming are under control. Patient balances. Missing files. Access questions nobody wanted to deal with yet. And that buys bad billing companies more time than they deserve. Even when the practice is already paying for it in the day-to-day stuff people get sick of fast. Time lost to follow-up. The same questions being asked again. Work drifting back into the office that should’ve stayed outside. But they keep putting it off because it is easier to say “not yet.” And the know the worst time to discover the real state of things is after the switch has already begun. Because handoffs create their own mess. Not from the switch itself. From everything nobody pinned down early enough. And that’s the difference between a handoff people dread and one they can actually get ready for. If someone is able to sit with the practice and say: here’s what’s denied, here’s what’s still open, here’s what’s missing, here’s who owns what, and here’s what has to get worked first. And that responsibility lies with the new billing company, which is why THAT is the main decision you need to think and worry about. Not all the minute details of the switch, handoff and execution. Or you can keep calling the current situation "safe". But in my experience, it usually means the team is already so drained and scared, that even the right move feels impossible. ----- If you're ready to have a conversation about switching, let's talk: https://lnkd.in/e7bNd8YV
- LINKEDIN · IMAGERecorded 2 Oct 2026
Every doctor should have to do the practice admin job for ONE day before they’re allowed to complain about how the clinic runs. Many industries figured this out decades ago. Every time someone has to do a seemingly easier job that is “beneath” them, they come out of the experience with a lot of perspective and appreciation. Medical Practices should run the same experiment. Because too many physicians talk and act like admin work is the easy part of running a practice. What makes it worse is how patients and the society at large thinks the same. This is why doctors get the respect, gratitude and more money. The practice admins get the pressure, the staffing mess, the scheduling mess, the insurance mess, the operational mess, and usually the attitude too. All for a much lower income... That is exactly why doctors should have to do this job, for at least one day every year. Answer the phones. Absorb the complaints. Deal with the scheduling mess. Carry the insurance nonsense. Get dumped on by everyone else for a few hours and then tell me again how "easy" it is. I'm confident one day would be enough to make them realize that most medical practices are being held together by practice admins who are underpaid and overused. I know making doctors do this job for one day won’t fix how patients deal with practice admins, or how the society at large thinks about them or erase all the other sh*t they have to absorb. But some doctors would stop believing this role is EASY or lesser than theirs. And that would be a small but welcome change...
- LINKEDIN · IMAGERecorded 2 Oct 2026
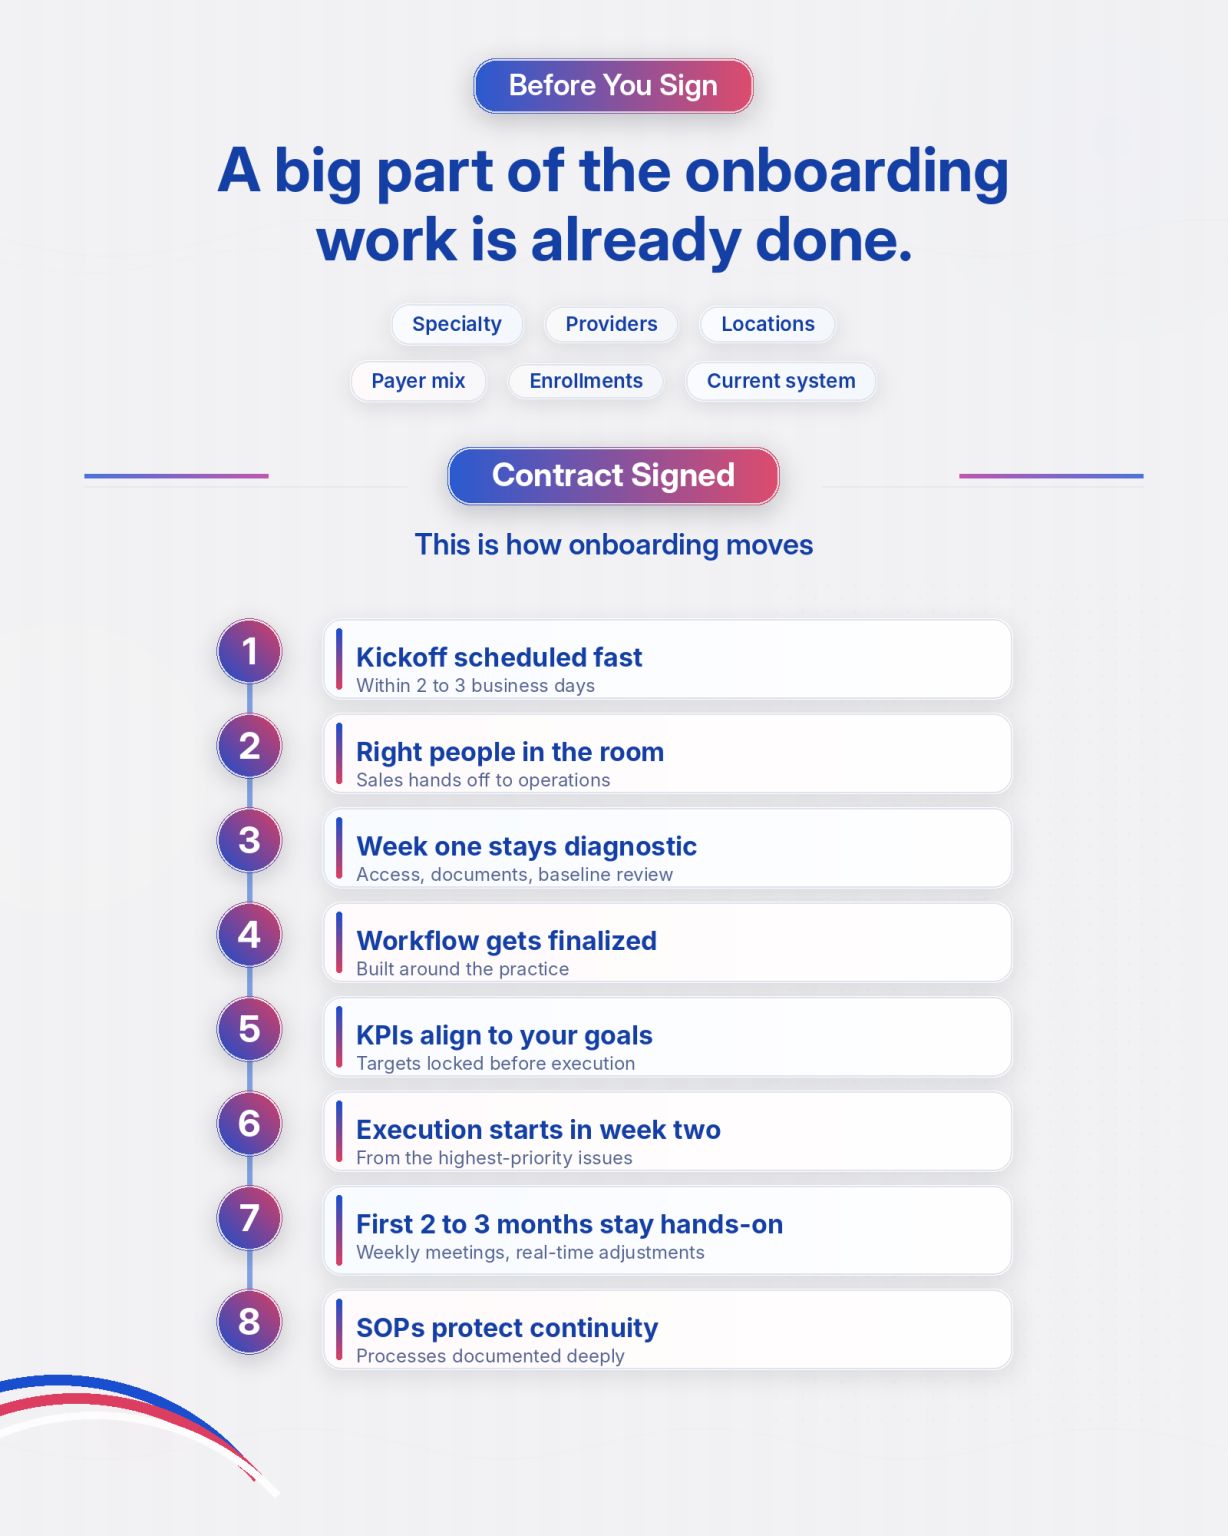
By the time you sign with us, a big part of our onboarding work is already done. Because the scoping starts long before the paperwork does. What specialty are we walking into? How many providers are involved? One location or several? What does the payer mix look like? Which enrollments are active, and which ones are still stuck? We always study the existing workflow, improve it, customize it around your practice, and build the proposal around that. Once the contract is signed, this is how the onboarding moves: 1. The kickoff gets scheduled quickly. Within 2 to 3 business days, the welcome call is arranged so the handoff starts moving immediately. 2. The right people enter the room Sales hosts the kickoff, makes the introductions, and then hands the discussion to operations. By the end of that call, you know your Account Manager in Pakistan, your Patient Contact Manager in the US, who is leading billing, who is leading credentialing, who owns BI/reporting, and where something goes if it needs escalation. 3. The first week stays diagnostic. Access and documents get collected. Then the team reviews the real starting point properly: what is sitting in A/R, what is already denied, what is stuck in enrollment, what is blocked by authorizations, unsigned charts, or practice-side dependencies. 4. The workflow gets finalized around the practice. This is where the proposal draft from discovery gets refined to become the live operating model. Communication paths, query handling, escalation flow, patient billing responsibilities, statement process, leadership visibility, and practice-side responsibilities all get locked in here. 5. Internal team KPIs get aligned with your goals before execution starts. Our team LITERALLY can't win until you do. So they get clear monthly KPIs built backwards from your goals. 6. Execution starts in week two, from the baseline priorities. It starts from what the first week exposed as most urgent and most fixable: A/R opportunities, denial patterns, enrollment holds, auth blockers, unsigned charts, and practice-side bottlenecks. 7. The first 2 to 3 months stay hands-on. With meetings every week. Real time workflow adjustments while the transition is still fresh. Once both sides agree the workflow is stable, the cadence shifts to fortnightly. 8. The whole system gets documented deeply into SOPs by the end of 3rd month If someone on our side is sick, out for a few days, or replaced later, your practice would not feel that even for a day. Because we build the SOPs with these exact situations in mind. The reason I'm sharing this is to show that onboarding doesn't have be chaotic for your practice or the medical billing company. It just needs a clear & structured process. And also because being accessible & transparent are core values of UControl Billing If you want a smooth onboarding like this, send me a DM :) Or book a call directly from calendar: https://lnkd.in/e7bNd8YV
- LINKEDIN · IMAGERecorded 2 Oct 2026
Billing is the easiest target in a medical practice. I’ve seen & heard enough stories to know that. An old insurance card stays on file. Eligibility gets “checked,” but not carefully enough. An authorization is assumed instead of confirmed. The visit gets documented, but not in a way that actually supports what was billed. On the day it happens, none of it looks dramatic. Then the denial shows up. The aging starts. The claim sits. And the moment words like denial, aging, or unpaid claim enter the conversation, billing gets pulled into the BLAME by default. This is exactly where practices misread the problem. I know nobody is waking up trying to create a revenue cycle problem. But that doesn't change what happens next. Billing ends up cleaning up someone else’s miss, absorbs the fallout and still gets blamed for damage that started earlier. Because you're fixing the symptom and protecting the cause. That is how practices end up with expensive rework, weeks of nonsense, and the same avoidable damage showing up again. It is lazy and unfair to dump this on billing when the leak started upstream. Strong billing work and teams matter a lot. But they CAN'T rescue bad intake, weak eligibility work, missing auth follow-up, or notes that do not support the claim. If the same denials keep repeating, I would stop staring at billing reports and start following the mistake backward. - Where was the insurance captured? - Who verified it? - What was actually authorized? - What does the note support? Practices improve faster once they stop using billing as the dumping ground for every problem. STOP using billing to hide your mistakes. Because it can absorb the fallout for a while but It will not fix a practice that keeps feeding it the same avoidable damage. If this keeps happening in your practice, the answer is probably sitting earlier in the workflow than everyone thinks. If you need help finding it, I'll audit your workflow for free. Book your free audit here: https://lnkd.in/e7bNd8YV





6 of 172 adsSign up to see every UControl Billing ad, filter by format and date, and get alerts on new ones.
See all 172 adsQuestions about UControl Billing’s ads
Is UControl Billing running LinkedIn ads?
We recorded no live LinkedIn ads for UControl Billing on 8 Nov 2026.
How many LinkedIn ads has UControl Billing run?
LinkedIn’s ad library lists 172 ads for UControl Billing. We recorded 172 LinkedIn ads for UControl Billing, first recorded on 2 Oct 2026 and last recorded on 2 Oct 2026.
Does UControl Billing advertise on Facebook and Instagram?
UControl Billing’s Facebook page had no active ads in Meta’s Ad Library, last recorded on 27 Oct 2026.
Does UControl Billing run Google ads?
Yes. We recorded 4 Google ads for the domain ucontrolbilling.com on 13 Oct 2026.
Which ad formats does UControl Billing use?
The 6 LinkedIn ads on this page include 6 image ads.
Watch the companies you care about.
Filter every ad by industry, country, format and network, and get alerts when a company you watch starts running new ads.